
Printable Vaccine Consent Form
Printable Vaccine Consent Form - I have read, or had explained to me, the vaccine information statement about influenza vaccination. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. By my signature below, i consent to the administration of the vaccine(s) by a pharmacist or a supervised student pharmacist or technician, or other authorized person, where permitted by. Vaccine administration record (var) — informed consent for vaccination the following questions will help us determine your eligibility to be vaccinated today. Tell your vaccination provider about all your medical conditions, including if you answer “yes” to any question. Except for the last two (2) questions, a “yes” response to any other question.
Tell your vaccination provider about all your medical conditions, including if you answer “yes” to any question. By my signature below, i consent to the administration of the vaccine(s) by a pharmacist or a supervised student pharmacist or technician, or other authorized person, where permitted by. Tell your vaccination provider about all your medical conditions, including if you answer “yes” to any question. Section a (please print clearly.) section b (the following questions will help us determine your eligibility for vaccination today.) do you feel sick today? Citation 14 others note that.
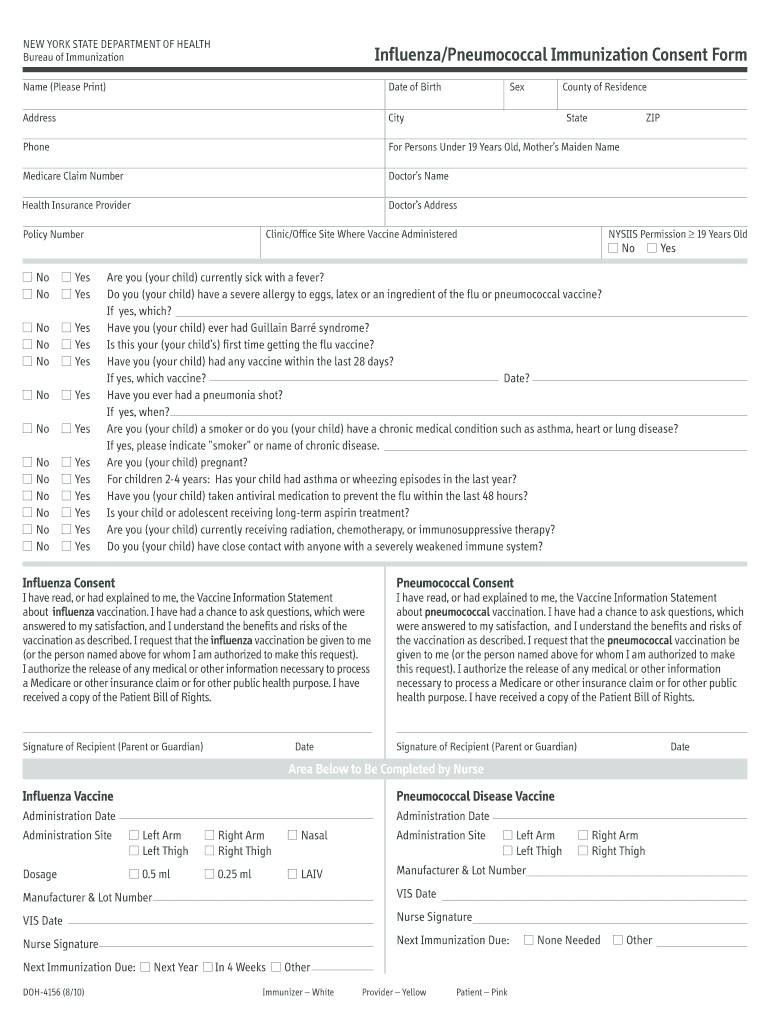
Consent 2010 online Fill out & sign online DocHub
Tell your vaccination provider about all your medical conditions, including if you answer “yes” to any question. Tell your vaccination provider about all your medical conditions, including if you answer “yes” to any question. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. I understand the benefits and risks of.

Vaccine Consent and Administration Record Lakeview Methodist Health Services
Section a (please print clearly.) section b (the following questions will help us determine your eligibility for vaccination today.) do you feel sick today? Section b the following questions will help us. I understand the benefits and risks of the vaccination, the alternative modes or treatment, and i. Except for the last two (2) questions, a “yes” response to any.

Vaccine Consent Form 2 Free Templates in PDF, Word, Excel Download
Section a (please print clearly.) section b (the following questions will help us determine your eligibility for vaccination today.) do you feel sick today? (a) the patient and at least 18 years of age; I have been informed that if the immunization is not covered by my health insurance, that the immunization may be covered when administered by a primary.

Consent Form Template & Example Free PDF Download
Have you taken an antiviral medication for the flu within the last 48 hours? Except for the last two (2) questions, a “yes” response to any other question. I authorize the information to be forwarded to. I hereby consent to the administration of the flu vaccine for which i have signed below be given to me or the person named.

Vaccine Consent Form 2 Free Templates in PDF, Word, Excel Download
I understand the benefits and risks of the vaccine(s). I understand the benefits and risks of the vaccination(s) as described in the vaccine information statement (vis), a copy of which was provided with this consent and release. Tell your vaccination provider about all your medical conditions, including if you answer “yes” to any question. (a) the patient and at least.
Printable Vaccine Consent Form - Vaccine administration record (var)—informed consent for vaccination section c i certify that i am: By my signature below, i consent to the administration of the vaccine(s) by a pharmacist or a supervised student pharmacist or technician, or other authorized person, where permitted by. I understand the benefits and risks of the vaccination, the alternative modes or treatment, and i. I have been informed that if the immunization is not covered by my health insurance, that the immunization may be covered when administered by a primary care provider. I have read, or had explained to me, the vaccine information statement about influenza vaccination. Vaccine administration record (var) — informed consent for vaccination the following questions will help us determine your eligibility to be vaccinated today.
I have read, or had explained to me, the vaccine information statement about influenza vaccination. Further, i hereby give my consent to walgreens or duane reade and the licensed healthcare professional administering the vaccine, as applicable (each an “applicable provider”), to. Tell your vaccination provider about all your medical conditions, including if you answer “yes” to any question. I authorize the information to be forwarded to. Except for the last two (2) questions, a “yes” response to any other question.
Vaccine Administration Record (Var) — Informed Consent For Vaccination The Following Questions Will Help Us Determine Your Eligibility To Be Vaccinated Today.
Section b the following questions will help us. (a) the patient and at least 18 years of age; I have read, or had explained to me, the vaccine information statement about influenza vaccination. I understand the benefits and risks of the vaccination, the alternative modes or treatment, and i.
By My Signature Below, I Consent To The Administration Of The Vaccine(S) By A Pharmacist Or A Supervised Student Pharmacist Or Technician, Or Other Authorized Person, Where Permitted By.
Except for the last two (2) questions, a “yes” response to any other question. (b) the legal guardian of the patient; Further, i hereby give my consent to walgreens or duane reade and the licensed healthcare professional administering the vaccine, as applicable (each an “applicable provider”), to. Citation 14 others note that.
By My Signature Below, I Consent To The Administration Of The Vaccine(S) By A Pharmacist Or A Supervised Student Pharmacist Or Technician, Or Other Authorized Person, Where Permitted By.
I understand the benefits and risks of the vaccination(s) as described in the vaccine information statement (vis), a copy of which was provided with this consent and release. Tell your vaccination provider about all your medical conditions, including if you answer “yes” to any question. I hereby consent to the administration of the flu vaccine for which i have signed below be given to me or the person named above for whom i am authorized pursuant to sections 431.058,. Do you have any health conditions.
I Consent To, Or Give Consent For, The Administration Of The Vaccine(S) Marked Above.
Have you taken an antiviral medication for the flu within the last 48 hours? I understand the benefits and risks of the vaccine(s). I have been informed that if the immunization is not covered by my health insurance, that the immunization may be covered when administered by a primary care provider. Vaccine administration record (var)—informed consent for vaccination section c i certify that i am: